

Key Takeaways
- The true cost of a third-party credentialing platform ranges from $0.70 to $3.00 per insured patient visit for most small and mid-sized practices. Sticker price is usually only 40 to 60% of that total.
- Four hidden layers drive the real cost: the platform tax of running two systems, tier gating of essential features, re-credentialing lapses, and delay-revenue loss from new provider hires.
- Solo and small practices often pay more per visit than large groups because credentialing costs scale with providers. A $6,000 platform is $1.80 per visit with two providers, but $0.27 per visit with five.
- Getting credentialed under your own name by a service provider usually beats standalone platforms on a per-visit cost basis for practices with fewer than 5 providers. Providers get exactly that when they sign up with PracticeEHR and chart and bill in the same system, without paying for credentialing or dozens of other tools.
You were quoted $200 a month for a credentialing platform. Fair enough. But that number hides something most vendors will not tell you: the real cost is not what shows up on the invoice. It is what leaks out of every patient visit for the next twelve months.
This article does the math nobody else on Google is doing. Instead of another list of per-provider fees, we will break down what a third-party credentialing platform actually costs you on a per-visit basis, why the sticker price is a lie, and when a standalone platform is worth it (spoiler alert: sometimes it is not).
If you are new to the credentialing timeline itself, read our companion piece first: How Long Does Provider Credentialing Take
The Formula Nobody Publishes
Here is what nobody tells you. To get your true cost per patient visit, add up all credentialing expenses for the year, then divide by the number of insured patient visits your practice sees that year.
True Cost Per Visit = (Platform fee + Setup + Add-ons + Delay revenue loss + Denial rework) ÷ Annual insured visits
Sounds obvious. So why does nobody walk through it? Because when you actually run the numbers, most third-party platforms look worse than they tell you.
Let’s go through the numbers!
A Real Worked Example
Consider a two-provider primary care practice. Each provider sees 20 patients a day, 220 working days a year. That is 8,800 annual patient visits. Roughly 85% are insured, so about 7,480 visits are billable to a payer.
Now, stack up the annual credentialing costs. The platform subscription is $6,000 a year. Setup was $1,500. Per-payer add-ons across four networks add another $800. So far, so predictable.
However, here is where it gets uncomfortable. Industry benchmarks put the revenue lost while a provider waits on enrollment at roughly $8,000 a month. This established practice adds providers rarely, so we'll use a conservative $4,000 for the year, plus about $1,200 in denial rework.
On top of that, denial rework from a lapsed license or a mismatched provider record runs around $25 to $118 per denied claim, depending on how deep the fix goes.
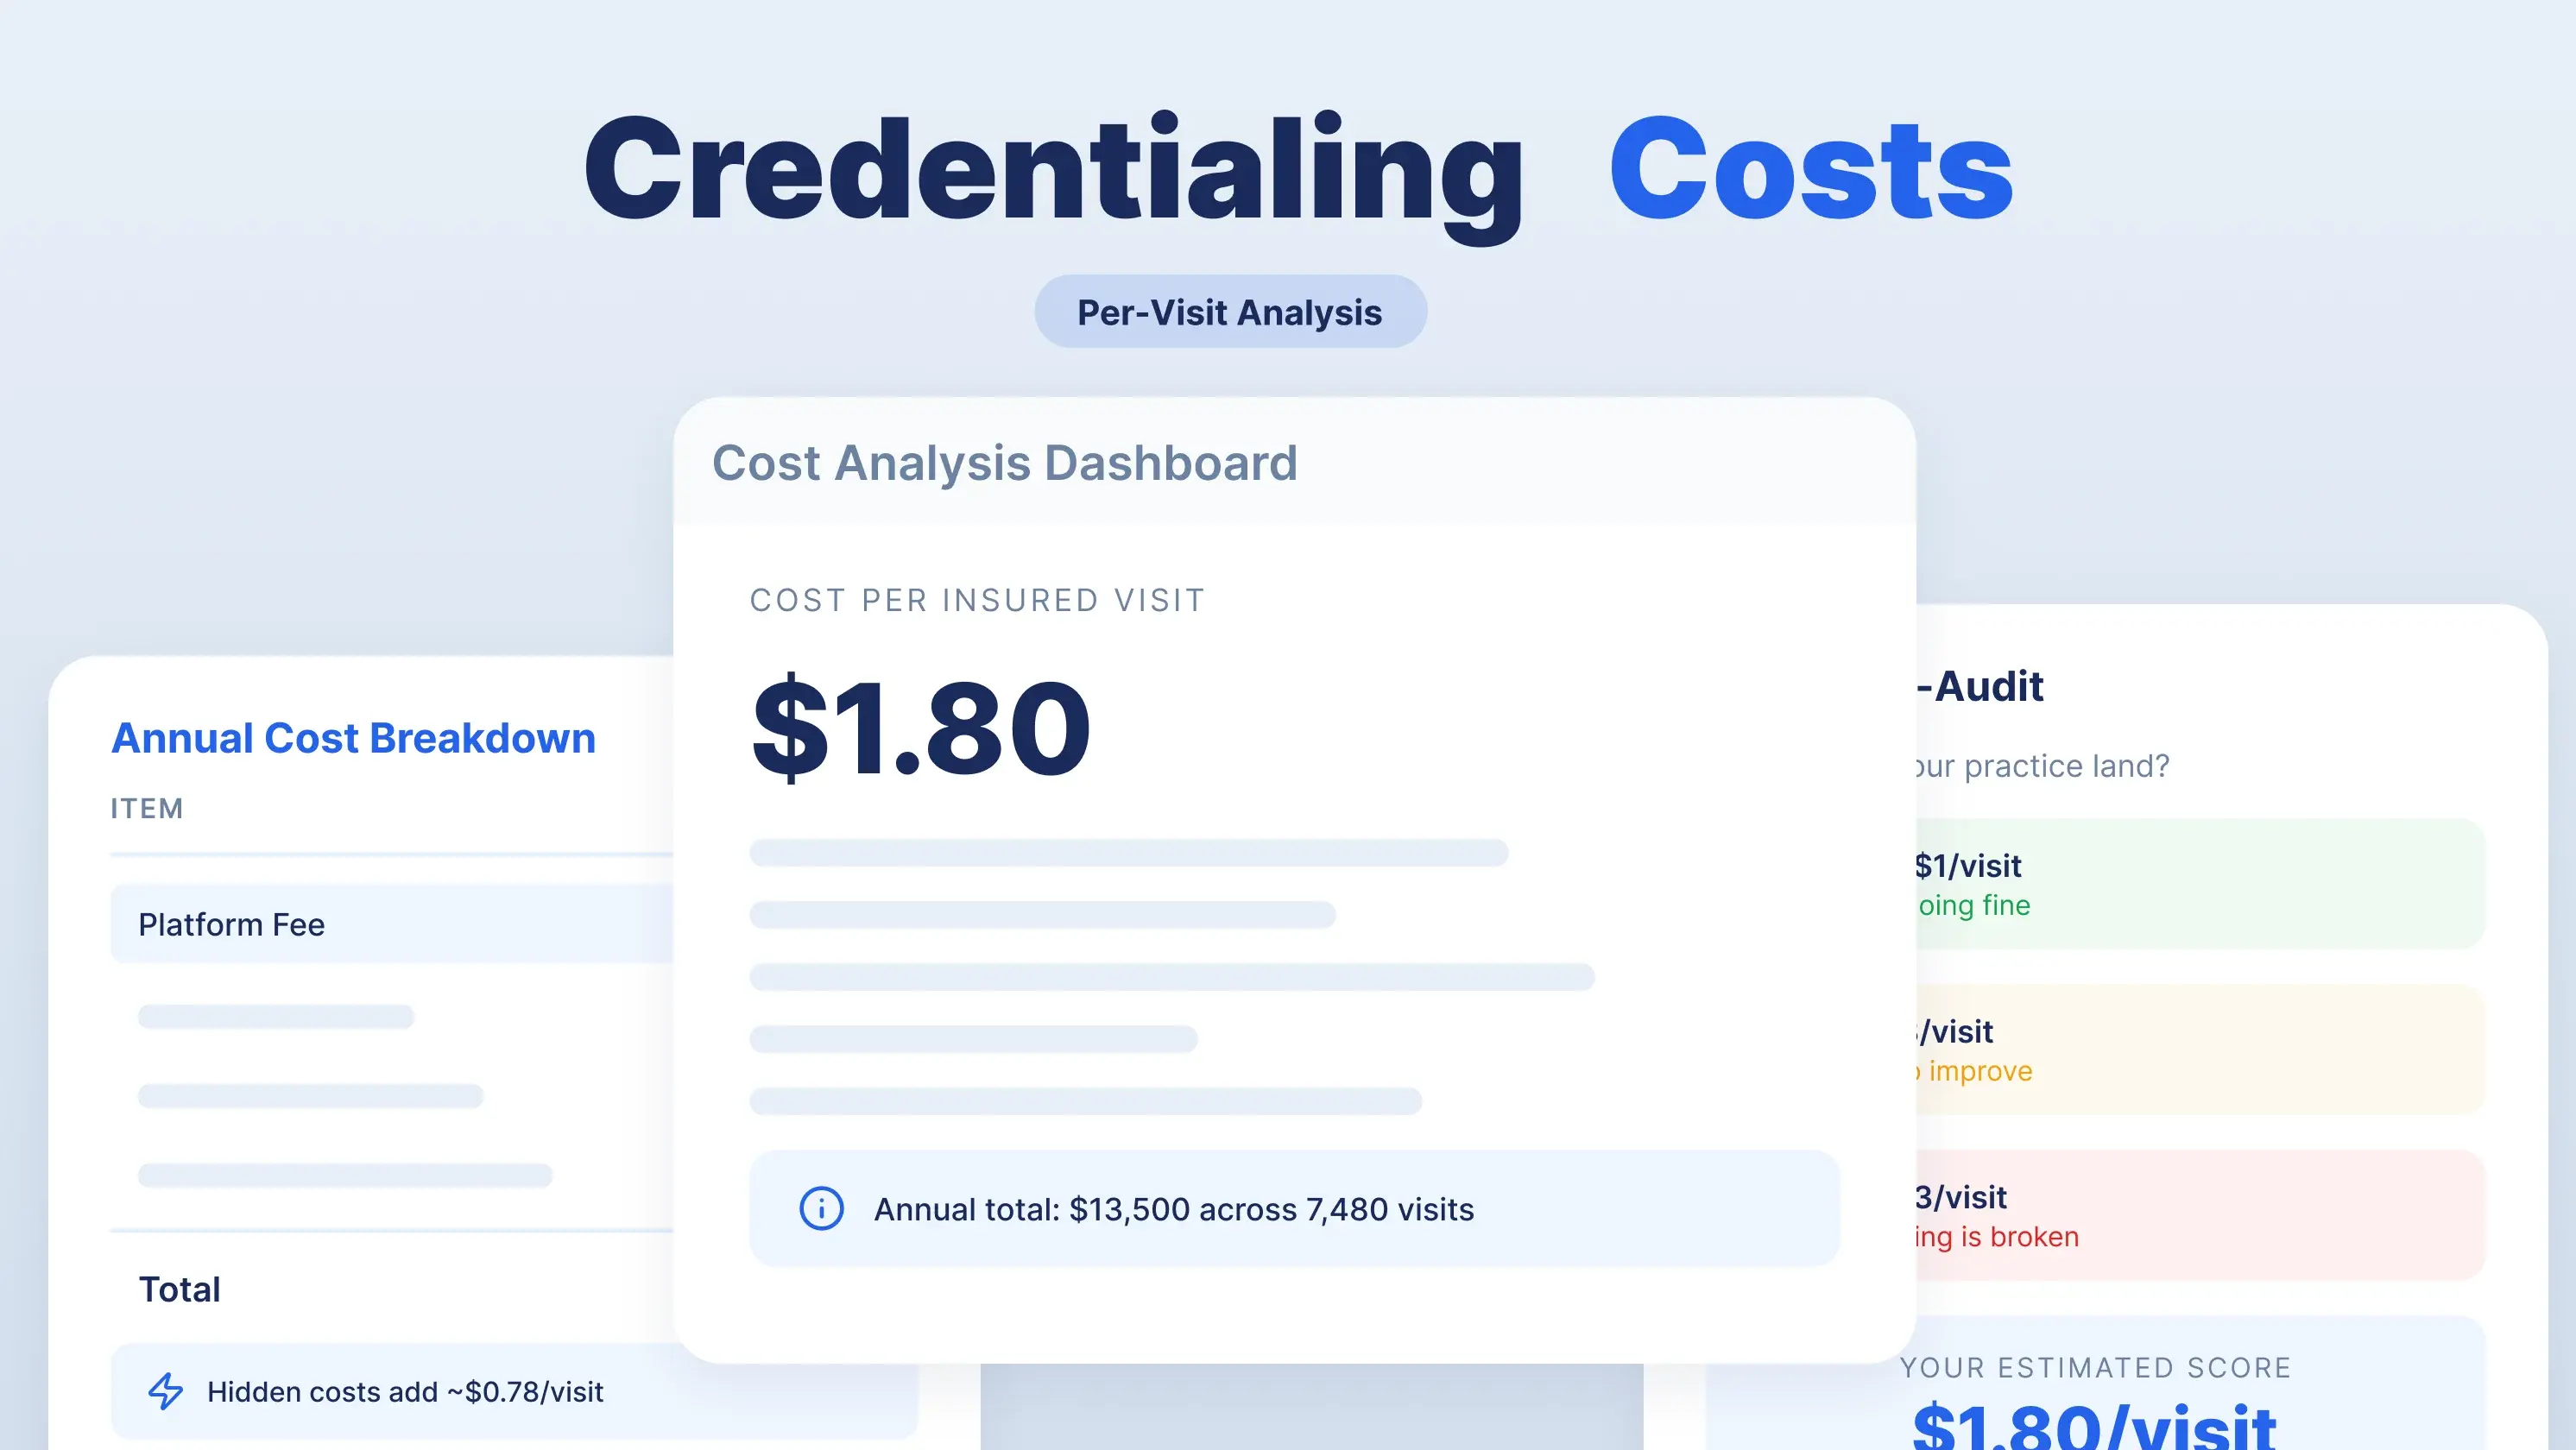
Add a modest $4,000 in delay costs and $1,200 in denial rework across the year. Your total credentialing spend is now $13,500.
Divide by 7,480 insured visits. That is $1.80 per patient visit.
Doesn't sound like much until you multiply it by every visit for the rest of your career. And it does not include the highest hidden cost, which we will get to in a moment.
What Most Calculations Leave Out
Go through all the third-party credentialing costs. Every single calculation focuses on cost per provider, cost per payer, or cost per application. Looking at it from that angle works for vendors because it makes their fees look insignificant next to a physician's salary. It does not work for you, because you do not bill by the provider. You bill by the visit.
Meanwhile, there are four cost layers that almost never show up in these calculations.
Layer 1: The platform tax
Every third-party credentialing platform sits outside your EHR and billing system. Consequently, your staff logs in separately, re-enters provider data, and syncs credential updates by hand. Sometimes that sync fails without any reason. Sometimes, a lapsed CDS certificate does not make it into the billing system, and claims start being denied. Nobody spots it for two weeks.
That drag has a cost that shows up later.
If your credentialing coordinator spends four hours a week logging between systems and reconciling records, at $28 an hour, that is roughly $5,800 a year. Spread across 7,480 visits, that is another $0.78 per visit. Nobody calls this a fee, but you are paying it anyway.
Layer 2: Tier gating
The sticker price you saw is usually the entry tier. Then you find out that expiration reminders, EDI setup, or scheduled reporting live in the next tier up. Hidden costs like setup fees, annual lock-in, and advanced features gated behind higher tiers can double the effective price of a platform that looks cheaper on paper. Ask any vendor for a full feature matrix before you sign. If they will not send one, that is your answer.
Layer 3: Re-credentialing surprises
Most payers require re-credentialing every 24 to 36 months. Miss the window, and you get dropped from the network. Getting back on takes 60 to 120 days, during which claims for that payer either deny or process at out-of-network rates.
In fact, the first missed re-credentialing deadline typically costs more than a full year of software, and network termination recovery runs $15,000 to $40,000. If your platform's reminder system is buried in a tier you did not buy, this is on you.
Layer 4: The delay tax on new hires
When you bring on a new provider, every day they cannot bill insured patients is a day of pure revenue leakage.
For example, a typical internist in the USA bills about $1,200 in insured visits per day once fully enrolled. With credentialing lag still running 60 to 90 days for Medicare, UnitedHealthcare, and Blue Cross Blue Shield, that is up to $108,000 in vanished revenue before your new doctor sees a single reimbursable patient.
A platform that shaves even ten days off that timeline pays for itself many times over. One that adds days by making your staff hunt for information is quietly costing you five figures per hire.
Platform-by-Platform Reality Check
While others just list platforms, quote a monthly price, and move on, let’s get a bit more specific about what you are actually paying at each tier in 2026.
Small-practice tools ($50 to $200 per month)
Basic tracking, expiration alerts, and document storage. These are useful if you have three or fewer providers and want to stop using a spreadsheet. Do not expect them to submit applications or chase payer follow-ups.
According to general 2026 benchmarks, small-practice tools for 1 to 5 providers cost anywhere from $50 to $200 per month for basic credential tracking software, while free tools like CAQH ProView handle data management..
Mid-market platforms ($200 to $500 per provider per month)
Real credentialing management with human oversight, primary source verification, active document collection, and dedicated liaisons. However, notice the pricing shifts to per-provider. At six providers, that $300 sticker price becomes $1,800 a month, or $21,600 a year. On a 25,000-visit practice, that is $0.86 per visit before you count staff time and integration gaps.
Enterprise platforms ($1,000 to $3,000+ per month)
Veritystream, CredentialStream, symplr sit here. Purpose-built for 20+ provider groups with dedicated credentialing staff. If you have three providers, this is overkill. If you have thirty, it is table stakes.
Managed services with a platform layer ($99 to $600 per provider per year)
Then there are flat-fee tiers offered by companies like CCS Pro at $99 per application for solo providers, OneExpert at $99 per first PPO panel application, and BillingAdvantage at $300 per provider, per insurance plan. This model bundles the software with the labor. Often, the better math if you do not want to staff for credentialing.
The cheapest option on paper is rarely the cheapest per visit. Conversely, the most expensive option is not automatically the best value either.
Solo vs. Group: the per-visit math changes everything
A solo family practitioner seeing 15 patients a day works out to about 3,300 annual visits. A $200-per-month platform costs $2,400 a year. That's $0.73 per visit before you factor in anything else. Not terrible.
Yet the same solo provider spending $5,000 a year on a fancier platform hits $1.52 per visit. Suddenly, the fancier platform needs to demonstrably save more than three staff hours a week or shave a week off a new payer enrollment. Otherwise, it is not worth it.
For a five-provider group at 22,000 annual visits, a $6,000 platform is $0.27 per visit. Much easier to justify. Scale matters. So, do not let a vendor sell you enterprise pricing on a solo practice budget.
When a Standalone Platform is Worth it
To be honest, sometimes a third-party credentialing platform earns its keep. Consider one if you meet at least two of these conditions:
-
You have five or more providers across multiple states.
-
You add or lose providers more than twice a year.
-
Your current credentialing coordinator is drowning, and your denial rate on eligibility issues is climbing.
-
You do multi-state telehealth and need license tracking across jurisdictions.
Otherwise, an EHR and practice management software that offers credentialing services will usually cost less per visit and cause fewer sync failures. Because a dedicated team handles the credentialing for you, you're not logging into a separate platform, re-entering provider data, or reconciling records by hand. Taking that work off your staff is what removes the platform tax.
Importantly, this is not a subtle plug. It is genuinely the answer for most small and mid-sized practices. When one team already handles your billing and does your credentialing for you, bolting a separate credentialing platform on top usually creates more work, not less.
The Five-Minute Self-Audit
Before you renew or sign anything, walk through this:
-
Add up every credentialing-related invoice from the last twelve months. Include platform fees, application fees, rush fees, and CAQH-related charges.
-
Estimate the delay revenue loss. Any provider who waited more than 45 days to bill a payer this year? Multiply the extra days by their daily billable revenue.
-
Estimate denial rework. Pull a report of claims denied for provider eligibility, credentialing, or enrollment issues. Multiply by $50 (a reasonable average per denial).
-
Add up staff hours spent on credentialing outside patient care. Multiply by the loaded hourly cost.
-
Divide by your annual insured visit count.
If your number is under $1 per visit, you are doing fine. Between $1 and $3, there is room to improve. Above $3, something is broken, either the platform, the process, or both.
Final Thoughts
Third-party credentialing platforms are sold on features. However, they should be evaluated on per-visit cost. Because you do not get paid by the provider, you get paid by the visit.
Consequently, the right platform is the one that lowers your actual per-visit credentialing cost, shortens enrollment timelines, and reduces denial rework. Sometimes, that is a dedicated credentialing SaaS.
Just as often, especially for small and mid-sized practices, it is an EHR and practice management provider, such as PracticeEHR, that includes credentialing as a done-for-you service when you sign up. Our team handles the applications and follow-ups, you bill on the same system, and you can see patients on cash or out-of-network while your panels come through.
Run your own numbers before your next renewal. If you would rather not maintain two systems, take a look at how PracticeEHR handles your credentialing for you, on the same platform you use to chart and bill.
FAQs


